
This page focuses on the neuropsychiatric manifestations associated with lesions of the dorsolateral prefrontal cortex (DLPFC).
Cognitive, behavioural, and psychiatric effects of lesions may also arise through mechanisms other than network disruption; the potential contribution of these mechanisms can be considered using the Neuropsychiatric Effects of CNS Structural Abnormalities (NECSA) classification.
Dorsolateral prefrontal cortex (DLPFC)
Page most recently updated 7 September 2026
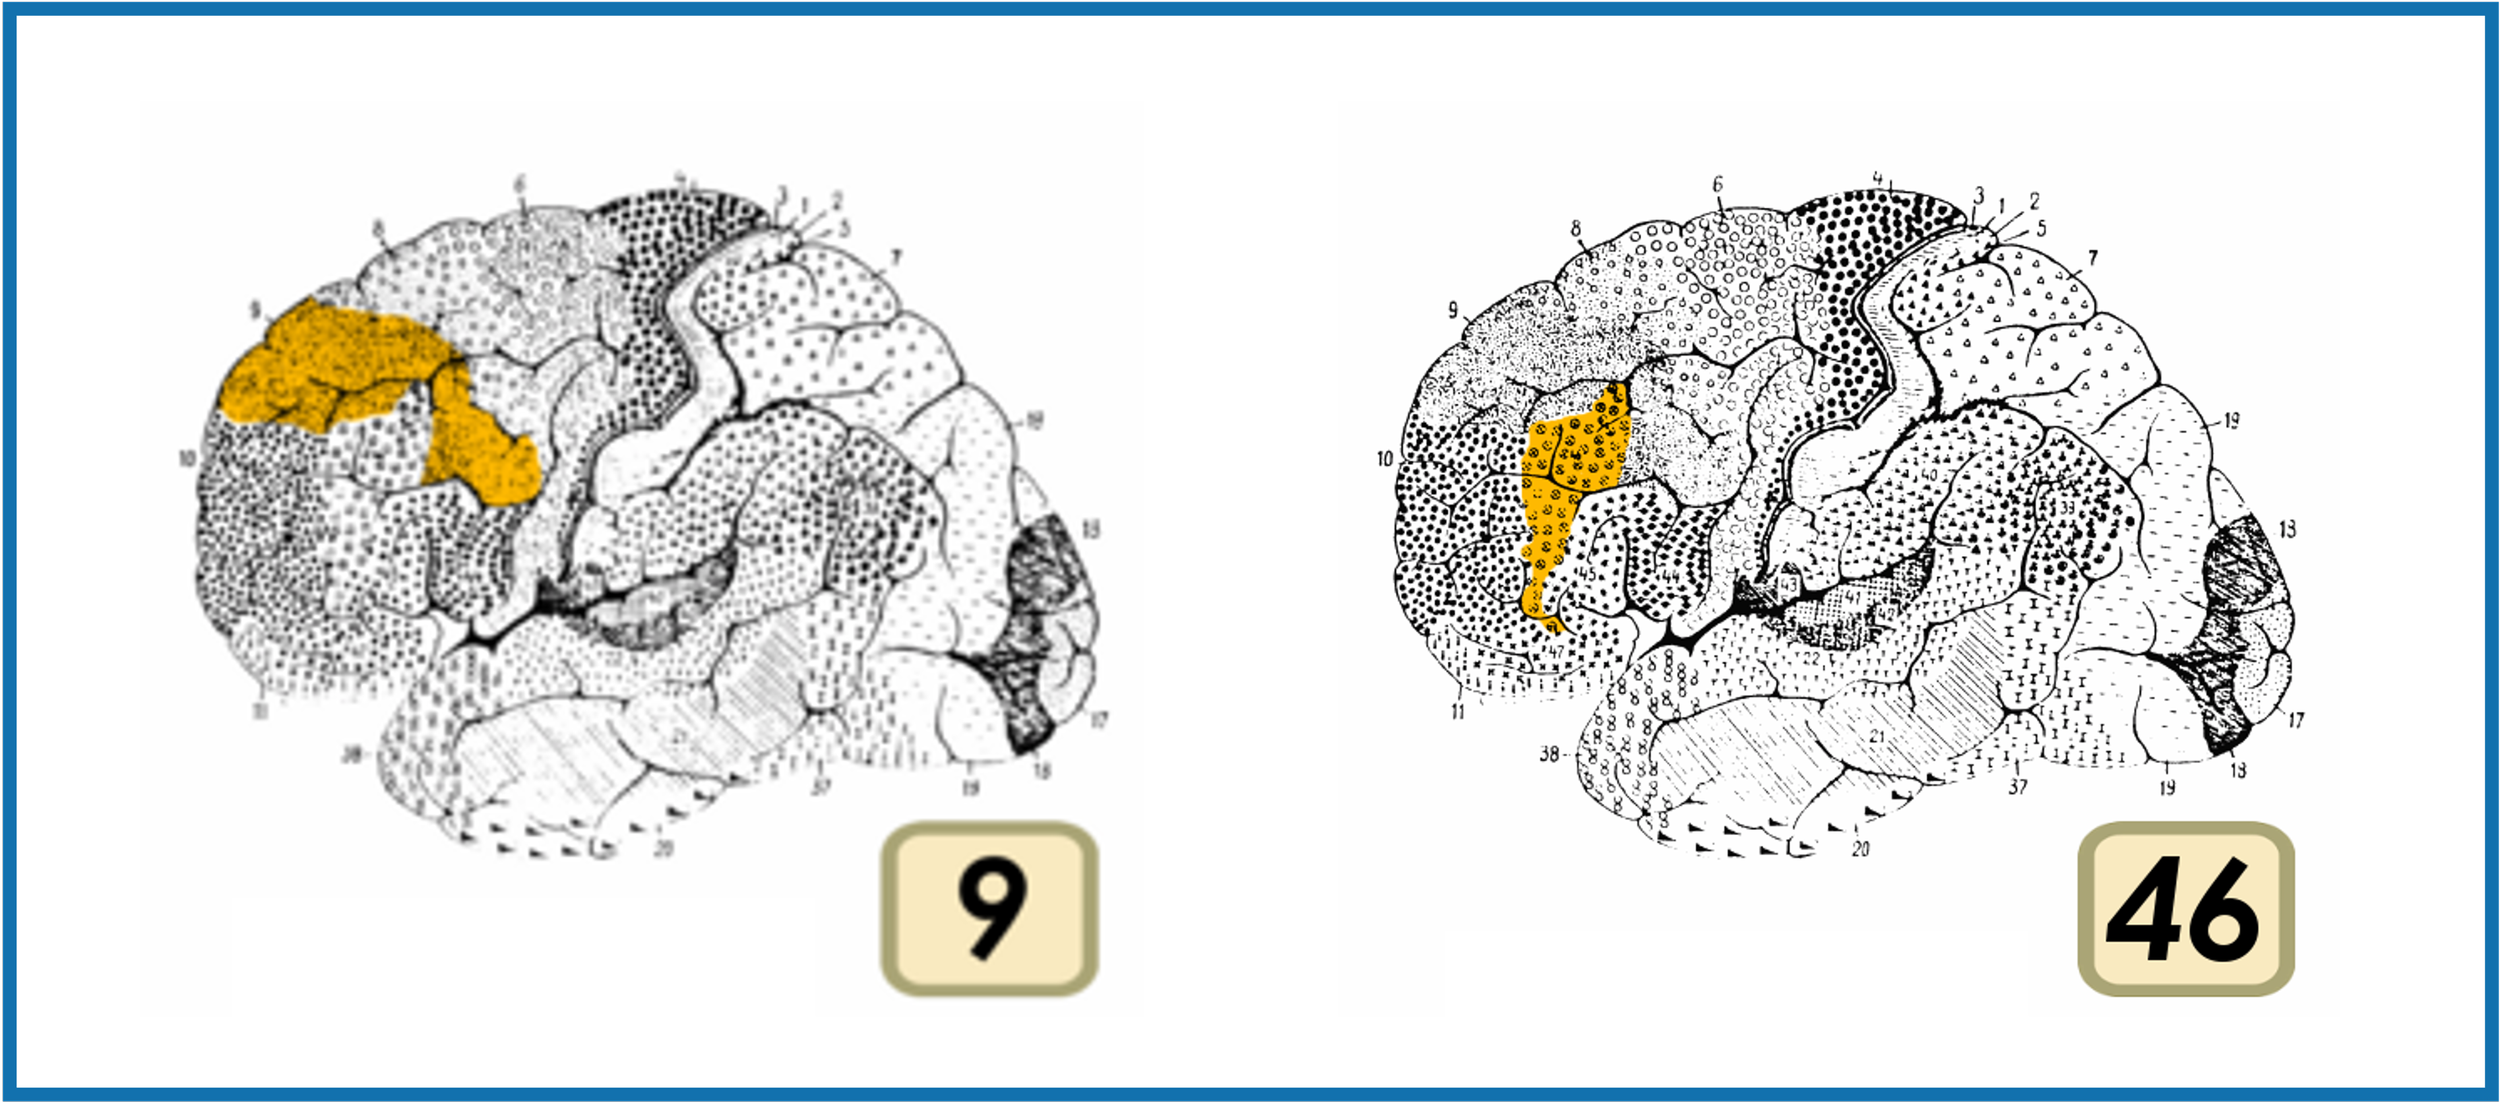
Dorsolateral prefrontal cortex (DLPFC)
Brodmann areas 9 and 46 are shown side by side, in lateral view, illustrating the cytoarchitectonic areas traditionally associated with the DLPFC. Boundaries vary between anatomical and functional parcellation schemes.
Image credit: Based on the cortical maps of Korbinian Brodmann. Public-domain image via Wikimedia Commons.
● Lesion manifestations
▪ Dysexecutive syndrome
▪ Poor planning
▪ Reduced cognitive flexibility
▪ Perseveration
▪ Difficulty multitasking
▪ Impaired abstraction
▪ Poor problem-solving
▪ Reduced insight into cognitive errors
▪ Patients may show:
◦ Intact basic memory but poor organisation of information
◦ Intact knowledge but impaired application
● Clinical pearls
▪ This is the prototypical region associated with "executive dysfunction."
▪ Patients may appear normal during conversation but fail when required to organise complex behaviour.
▪ DLPFC dysfunction is common after TBI and may be mistaken for depression, poor motivation, or personality change.
Clinical reminder: consider NECSA mechanisms
(Neuropsychiatric Effects of CNS Structural Abnormalities)
When a structural lesion is identified in a patient presenting with neuropsychiatric symptoms, consider which NECSA mechanisms may explain these symptoms:
● Network disruption
Disruption of functional networks due to the presence of the lesion
● Electrical disturbance
Ictal, preictal, postictal, or interictal effects due to epileptic activity associated with the lesion (particularly if involving or adjacent to cortex)
● Chemical (endocrine) effects
Hormone excess or deficiency caused by the lesion (particularly if involving the pituitary gland or hypothalamus)
● Side effects of treatment
Effects of medications, surgery, radiotherapy, or other interventions
● Alternative explanations
The lesion may be incidental, or symptoms may arise from another cause (e.g., psychological response to illness or a comorbid psychiatric condition)
Selected references and further reading — Lesional lens
Rohlfing T, Zahr NM, Sullivan EV, Pfefferbaum A. The SRI24 multichannel atlas of normal adult human brain structure. Hum Brain Mapp. 2010;31(5):798–819.
Clark DL, Boutros NN, Mendez MF. The brain and behavior: an introduction to behavioral neuroanatomy. 4th ed. Cambridge: Cambridge University Press; 2018.
Brazis PW, Masdeu JC, Biller J. Localization in clinical neurology. 7th ed. Philadelphia: Wolters Kluwer/Lippincott Williams & Wilkins; 2016.
Blumenfeld H. Neuroanatomy through clinical cases. 3rd ed. New York: Oxford University Press; 2021.
Hassan I. The neuropsychiatric effects of CNS structural abnormalities (NECSA) classification: an aid to differential diagnosis. Aust N Z J Psychiatry. 2015;49(10):943.
Arciniegas DB, Yudofsky SC, Hales RE, editors. The American Psychiatric Association Publishing textbook of neuropsychiatry and clinical neurosciences. 6th ed. Washington (DC): American Psychiatric Association Publishing; 2018.
Agrawal N, Faruqui R, Bodani M, editors. Oxford textbook of neuropsychiatry. Oxford: Oxford University Press; 2020.