
This page focuses on the neuropsychiatric manifestations associated with lesions of the frontal aslant tract (FAT).
Cognitive, behavioural, and psychiatric effects of lesions may also arise through mechanisms other than network disruption; the potential contribution of these mechanisms can be considered using the Neuropsychiatric Effects of CNS Structural Abnormalities (NECSA) classification.
Frontal aslant tract (FAT)
Page most recently updated 7 September 2026
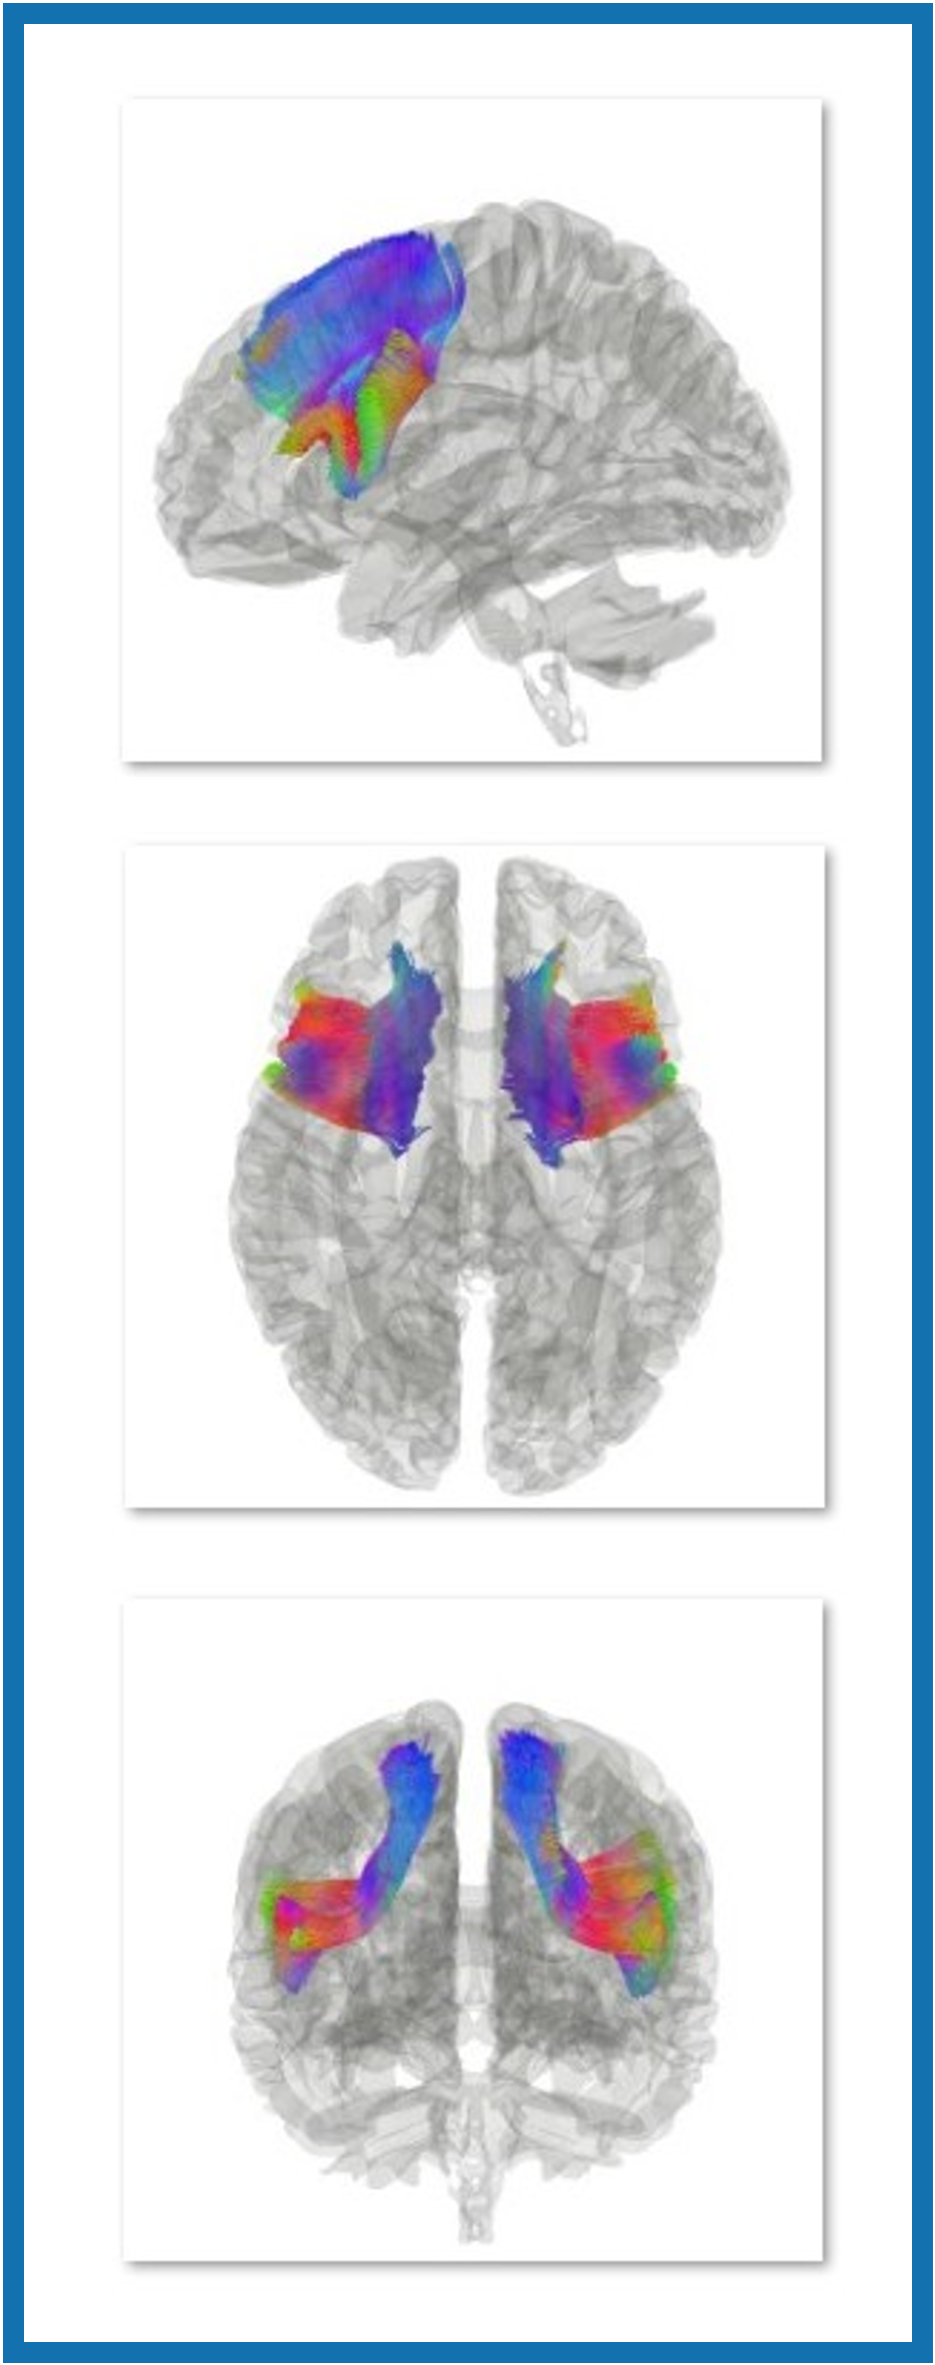
Frontal aslant tract
The tract is shown in sagittal, axial, and coronal views.
Image credit: Adapted from Yeh et al. (2018), Population-averaged atlas of the macroscale human structural connectome and its network topology. CC BY-SA 4.0, via Wikimedia Commons.
● Lesion manifestations
▪ Speech initiation impairment
▪ Reduced verbal fluency
▪ Dynamic aphasia (reduced spontaneous speech despite relatively preserved comprehension and repetition)
▪ Apraxia of speech (impaired planning and sequencing of speech movements; patients may produce individual sounds such as “pa,” “ta,” and “ka” but struggle to combine them into sequences such as “pataka”)
▪ Reduced internally generated behaviour
● Clinical pearls
▪ FAT lesions can create a disconnect between knowing what to say or do and being able to spontaneously generate speech and behaviour. This can mimic psychiatric syndromes such as apathy or reduced motivation, even when the frontal cortex itself appears relatively preserved.
▪ Particularly relevant in neurosurgical planning for dominant frontal tumours.
Clinical reminder: consider NECSA mechanisms
(Neuropsychiatric Effects of CNS Structural Abnormalities)
When a structural lesion is identified in a patient presenting with neuropsychiatric symptoms, consider which NECSA mechanisms may explain these symptoms:
● Network disruption
Disruption of functional networks due to the presence of the lesion
● Electrical disturbance
Ictal, preictal, postictal, or interictal effects due to epileptic activity associated with the lesion (particularly if involving or adjacent to cortex)
● Chemical (endocrine) effects
Hormone excess or deficiency caused by the lesion (particularly if involving the pituitary gland or hypothalamus)
● Side effects of treatment
Effects of medications, surgery, radiotherapy, or other interventions
● Alternative explanations
The lesion may be incidental, or symptoms may arise from another cause (e.g., psychological response to illness or a comorbid psychiatric condition)
Selected references and further reading — Lesional lens
Rohlfing T, Zahr NM, Sullivan EV, Pfefferbaum A. The SRI24 multichannel atlas of normal adult human brain structure. Hum Brain Mapp. 2010;31(5):798–819.
Clark DL, Boutros NN, Mendez MF. The brain and behavior: an introduction to behavioral neuroanatomy. 4th ed. Cambridge: Cambridge University Press; 2018.
Brazis PW, Masdeu JC, Biller J. Localization in clinical neurology. 7th ed. Philadelphia: Wolters Kluwer/Lippincott Williams & Wilkins; 2016.
Blumenfeld H. Neuroanatomy through clinical cases. 3rd ed. New York: Oxford University Press; 2021.
Hassan I. The neuropsychiatric effects of CNS structural abnormalities (NECSA) classification: an aid to differential diagnosis. Aust N Z J Psychiatry. 2015;49(10):943.
Arciniegas DB, Yudofsky SC, Hales RE, editors. The American Psychiatric Association Publishing textbook of neuropsychiatry and clinical neurosciences. 6th ed. Washington (DC): American Psychiatric Association Publishing; 2018.
Agrawal N, Faruqui R, Bodani M, editors. Oxford textbook of neuropsychiatry. Oxford: Oxford University Press; 2020.